
By Christopher Piercecchi, MD — Physician and Wellness Manager, Founder, The Men’s Clinic for Wellness & Vitality
Bottom Line Up Front (BLUF): A physician and photobiomodulation (PBM) advocate published a detailed rebuttal to my original review of red light therapy. His argument isn’t that I got the science wrong; he says as much himself. His argument is that I “reviewed a broad consumer product category, “red light therapy,” and let that verdict spill over onto a precisely dosed, physician-directed clinical intervention I never actually examined.”
Let me be clear about something up front. He’s right that this isn’t a dispute over the underlying evidence; he says so directly. Where we disagree is what follows from that. He treats the category distinction he’s identified as fatal to my conclusion. It isn’t, and there’s at least one place where his own definition of the “real” intervention goes further than the evidence he cites can support. So I went back through his arguments and the underlying evidence, point by point. This article is my response and an attempt to correct the record where his critique mischaracterizes what I wrote or goes beyond what the evidence actually shows.
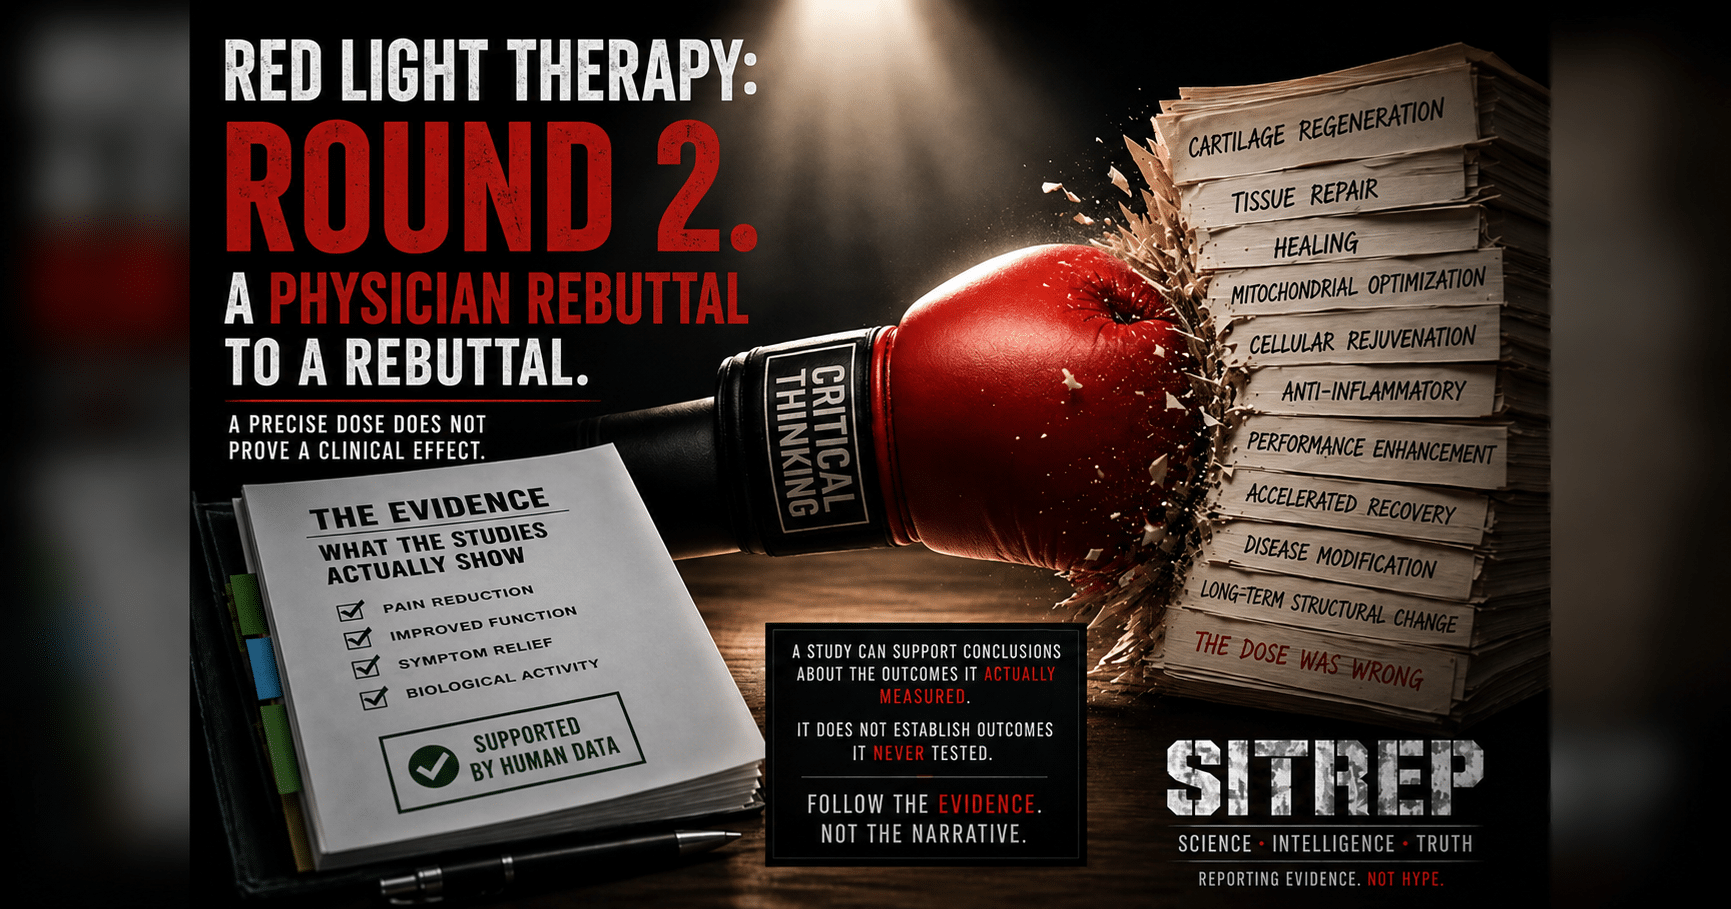
The central issue between him and me is simple. He reiterates that dose, wavelength, delivery, tissue penetration, and biological plausibility all matter. And I agree. They do. But my point, and what he doesn’t seem to understand, is that getting those things right only establishes what treatment was delivered. It does not establish whether that treatment produces the claimed clinical outcome. A precisely delivered therapy can still fail, and a negative result cannot simply be explained away after the fact by assuming the dose or delivery must have been wrong.
Human evidence supports PBM for some specific outcomes, including oral mucositis and selected improvements in pain. But the evidence for function and exercise recovery is limited and arguable.[4,5,8,15] Moreover, the orthopedic evidence remains inconsistent and often low certainty, and it does not convincingly demonstrate regeneration of lost cartilage, structural tendon healing, or improved outcomes from adding PBM to platelet-rich plasma (PRP) or other orthobiologic treatments.[5,9,11,13,14,18,19]
Biological plausibility is not clinical efficacy. Symptom improvement is not structural regeneration. And a precise dose is not proof that the treatment does what is being claimed.
The wavelength may be the signal. The dose may be the prescription. But a precise prescription still has to be shown to produce the clinical outcome it is supposed to produce.
Consider subscribing to read my detailed, fully referenced response. Red Light Therapy: Round 2 starts below.
Back to All Blogs